Tag: MINOCA

Research

2023 ESC Guidelines for the management of acute coronary syndromes:...

Guidelines evaluate and summarize available evidence with the aim of assisting health professionals in proposing the best diagnostic or therapeutic approach for an individual patient with a given condition. Guidelines are intended for use by health professionals and the European Society of Cardiology (ESC) makes its Guidelines freely available. ESC Guidelines do not override the individual responsibility of health professionals to make appropriate and accurate decisions in consideration of each patient’s health condition and in consultation with that patient or the patient’s caregiver where appropriate and/or necessary.
Read More »
Research

Stratified treatment of myocardial infarction with non-obstructive coronary arteries: the...

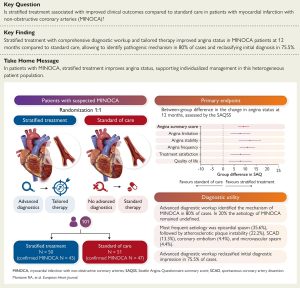
Myocardial infarction with non-obstructive coronary arteries (MINOCA) is associated with a significant risk of mortality, rehospitalization, and angina burden. Despite its clinical impact, no randomized clinical trials have hitherto evaluated optimal management strategy for MINOCA. The PROMISE trial was designed to assess whether a stratified treatment improves clinical outcomes in patients with MINOCA as compared to standard care.

Read More »
Research

Societal, occupational, and economic considerations for women with (M)INOCA: a...

Cardiovascular disease is one of the leading causes of mortality in women, despite underrepresentation in the medical literature. Women have higher rates of ischemia and no obstructive coronary artery disease (INOCA) and myocardial infarction with no obstructive coronary artery disease (MINOCA) compared to men. The aim of this review is to describe the occupational, economic, and psychosocial factors which disproportionately impact women with (M)INOCA.

Read More »
Research

Functional Coronary Angiography for the Diagnosis of Coronary Vasomotor Disorders

Microvascular and/or vasospastic angina are two common forms of coronary vasomotor disorders that may occur in patients with ischaemia and non-obstructed coronary arteries (INOCA) or myocardial infarction with non-obstructive coronary arteries (MINOCA).

Functional coronary angiography involves invasive guidewire-based assessment of the coronary circulation using pharmacological vasoactive agents to assess small and large vasomotor dysfunction. Typically, responses to adenosine (microvascular vasodilator) and acetylcholine (large and small vessel vasospastic agent) are sequentially assessed.

Read More »
Research

Exploring patients’ views regarding the support and rehabilitation needs of...

This study aimed to generate new qualitative insights to understand the rehabilitation needs of people living with a confirmed or presumed diagnosis of ischaemia with no obstructive coronary arteries (INOCA), explore which aspects of current cardiovascular prevention and rehabilitation programmes could meet the needs of people with INOCA and where adjustments (if any) may be appropriate.

Read More »
Research

Stratified medicine for acute and chronic coronary syndromes: A patient-tailored...

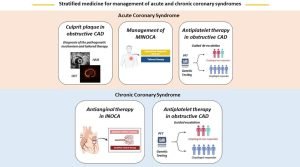
The traditional approach to management of cardiovascular disease relies on grouping clinical presentations with common signs and symptoms into pre-specified disease pathways, all uniformly treated according to evidence-based guidelines (“one-size-fits-all”). The goal of precision medicine is to provide the right treatment to the right patients at the right time, combining data from time honoured sources (e.g., history, physical examination, imaging, laboratory) and those provided by multi-omics technologies. In patients with ischemic heart disease, biomarkers and intravascular assessment can be used to identify endotypes with different pathophysiology who may benefit from distinct treatments. This review discusses strategies for the application of stratified management to patients with acute and chronic coronary syndromes.

Read More »
Research

Predicting the response to acetylcholine in ischemia or infarction with...

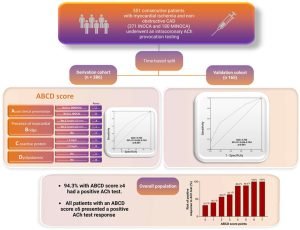
Acetylcholine (ACh) provocation testing can detect vasomotor disorders in patients with ischemia and non-obstructed coronary arteries (INOCA) or myocardial infarction and non-obstructed coronary arteries (MINOCA). We aimed to derive and validate a simple risk score to predict a positive ACh test response.

We prospectively enrolled consecutive INOCA and MINOCA patients undergoing ACh provocation testing. Patients were split in two cohorts (derivation and validation) according to time of enrolment. The score was derived in 386 patients (derivation cohort) and then validated in 165 patients (validation cohort).

Read More »
Research

ANOCA/INOCA/MINOCA: Open artery ischemia

Ischemic heart disease continues to represent a major health threat for death, disability, and poor quality of life as it also consumes enormous health-related resources. For over a century, the major clinical phenotype was taken to be obstructive atherosclerosis involving the larger coronary arteries (e.g., coronary artery disease [CAD]). However, evolving evidence now indicates that nonobstructive CAD is the predominant phenotype.

Patients within this phenotype have been termed to have angina with no obstructive CAD (ANOCA), ischemia with no obstructive CAD (INOCA), or myocardial infarction with no obstructive coronary arteries (MINOCA). But as methods to assess cardiomyocyte injury evolve, these phenotypic distinctions have begun to merge, raising concern about their usefulness.

Read More »
Research

What an Interventionalist Needs to Know About MI with Non-obstructive...

MI with non-obstructive coronary arteries (MINOCA) is caused by a heterogeneous group of vascular or myocardial disorders. MINOCA occurs in 5–15% of patients presenting with acute ST-segment elevation MI or non-ST segment elevation MI and prognosis is impaired.

The diagnosis of MINOCA is made during coronary angiography following acute MI, where there is no stenosis ≥50% present in an infarct-related epicardial artery and no overt systemic aetiology for the presentation. Accurate diagnosis and subsequent management require the appropriate utilisation of intravascular imaging, coronary function testing and subsequent imaging to assess for myocardial disorders without coronary involvement.

Read More »
Research

Interplay Between Myocardial Bridging and Coronary Spasm in Patients With...

Myocardial bridging (MB) may represent a cause of myocardial ischemia in patients with non‐obstructive coronary artery disease (NOCAD). Herein, we assessed the interplay between MB and coronary vasomotor disorders, also evaluating their prognostic relevance in patients with myocardial infarction and non‐obstructive coronary arteries (MINOCA) or stable NOCAD.

We prospectively enrolled patients with NOCAD undergoing intracoronary acetylcholine provocative test. The incidence of major adverse cardiac events, defined as the composite of cardiac death, non‐fatal myocardial infarction, and rehospitalization for unstable angina, was assessed at follow‐up.

Read More »
Research

Assessment of Vascular Dysfunction in Patients Without Obstructive Coronary Artery...

Ischemic heart disease secondary to coronary vascular dysfunction causes angina and impairs quality of life and prognosis. About one-half of patients with symptoms and signs of ischemia turn out not to have obstructive coronary artery disease, and coronary vascular dysfunction may be relevant.

Adjunctive tests of coronary vasomotion include guidewire-based techniques with adenosine and reactivity testing, typically by intracoronary infusion of acetylcholine. The CorMicA (Coronary Microvascular Angina) trial provided evidence that routine management guided by an interventional diagnostic procedure and stratified therapy improves angina and quality of life in patients with angina but no obstructive coronary artery disease.

Read More »
Around The World

Real Patient Stories

Lynn’s story

I had my first spasm when I was just a young child and continued for almost 50 years with no diagnosis. I always assumed everybody had flushing feelings throughout their body, and hot flashes accompanied by chest pain.

It wasn’t until I was walking my dogs with my sister, one day, and we were going up a steep incline and I couldn’t keep up. I asked her if she felt chest pains when she walked up hills. She looked at me like I was crazy and told me: No!

I then realized something might be wrong with me.

Read More »

Dima’s story

March 3rd, 2021 was the day that changed everything. At 55, I had a busy counselling practice and a few other projects on the go. The pandemic was causing anxiety for many of my clients and in my private life. I had a lot of stress of my own: there were safety issues in the building where I lived, and I was looking for a new apt. Despite this, I thought I was handling it well. I was fairly healthy, I walked daily, ate well, meditated and didn’t smoke or drink.

I started to experience heavy fatigue towards the end of 2020 but told myself it was normal considering all that was going on in the world.

Read More »

Barbara’s story

I am a 62-year-old retired physician. My story began at age 47.

I was a very busy practicing OB/Gyn physician who was otherwise healthy.

I was on call at the hospital, and it was turning out to be one of the busiest days I had ever experienced as a physician. I was in a medical group that took call for 24 hours straight, most of the time working the entire 24 hours.

Halfway through that 24-hour call, I was in the operating room doing a C/Section on a patient. Halfway through the surgery I began to feel crushing chest pain.

Read More »

Get Informed

Learn all about the symptoms, causes and triggers of these heart conditions.

Educate. Inform. Enlighten.