Tag: ischaemia

Research

Endotyping-informed therapy for patients with chest pain and no obstructive...

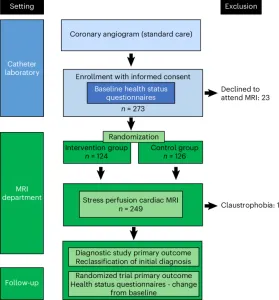
Patients undergoing invasive coronary angiography for the investigation of chest pain commonly do not have obstructive coronary artery disease. In contemporary practice, most of these individuals do not undergo functional diagnostic tests, leaving the cause of the chest pain uncertain. Stress cardiovascular magnetic resonance imaging (MRI) can be used to measure myocardial blood flow, detect coronary microvascular dysfunction and endotype individual patients, but evidence of clinical utility from randomized trials is lacking. This study was a prospective, multicenter, parallel group, 1:1 randomized, controlled superiority trial of adenosine stress cardiovascular MRI-guided management in 250 patients (mean age, 63.3 years; 50.4% female) with chest pain and unobstructed coronary arteries.
Read More »
Research

Novel therapy for ischaemia with no obstructive coronary arteries

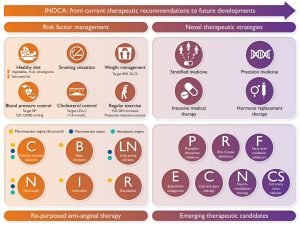
Coronary vascular dysfunction causes microvascular angina and vasospastic angina, which are prevalent clinical endotypes of myocardial ischaemia with no obstructive coronary arteries (INOCA). INOCA impairs quality of life and confers an increased likelihood of cardiovascular events and health resource utilization.

Contemporary advances in non-invasive and invasive testing facilitate an accurate diagnosis and linked therapy. New guideline recommendations and patient advocacy are also relevant. Nonetheless, a lack of disease-modifying therapy for INOCA perpetuates the medical need.

Read More »
Research

Management of ischaemia with non-obstructive coronary arteries (INOCA)

Up to half of patients undergoing elective coronary angiography for the investigation of chest pain do not present with evidence of obstructive coronary artery disease. These patients are often discharged with a diagnosis of non-cardiac chest pain, yet many could have an ischaemic basis for their symptoms. This type of ischaemic chest pain in the absence of obstructive coronary artery disease is referred to as INOCA (ischaemia with non-obstructive coronary arteries).

This comprehensive review of INOCA management looks at why these patients require treatment, who requires treatment based on diagnostic evaluation, what clinical treatment targets should be considered, how to treat patients using a personalised medicine approach, when to initiate treatment, and where future research is progressing.

Read More »
Research

How to Diagnose and Manage Angina Without Obstructive Coronary Artery...

Patients with symptoms and/or signs of ischaemia but no obstructive coronary artery disease (INOCA) present a diagnostic and therapeutic challenge. Microvascular and/or vasospastic angina are the two most common causes of INOCA; however, invasive coronary angiography lacks the sensitivity to diagnose these functional coronary disorders.

In this article, the authors summarise the rationale for invasive testing in the absence of obstructive coronary disease, namely that correct treatment for angina patients starts with the correct diagnosis. They provide insights from the CORonary MICrovascular Angina (CorMicA) study, where an interventional diagnostic procedure was performed with linked medical therapy to improve patient health.

Read More »
Research

Systemic microvascular dysfunction in microvascular and vasospastic angina

Coronary microvascular dysfunction and/or vasospasm are potential causes of ischaemia in patients with no obstructive coronary artery disease (INOCA). We tested the hypothesis that these patients also have functional abnormalities in peripheral small arteries.

Patients were prospectively enrolled and categorised as having microvascular angina (MVA), vasospastic angina (VSA) or normal control based on invasive coronary artery function tests incorporating probes of endothelial and endothelial-independent function (acetylcholine and adenosine).

Read More »
Around The World

Real Patient Stories

Sinéad’s story

My first episode caught me completely off guard on a Sunday morning in 2014. I was an active, healthy 35-year-old mother of 3. It felt like what I imagined having a heart attack would feel like. After a minute or two it stopped as suddenly as it had started and I got out of bed to start my day, I had experienced palpitations before and brushed it off as a once off.

I had about 8 more episodes before lunch time and made a deal with myself that if it continued, I would call an ambulance. I was a busy mum and didn’t want to be ‘dramatic’! It resolved by 2 p.m.

Read More »

MaryAnn’s story

When I was 39, with zero risk factors for heart disease, I had all the classic symptoms associated with a heart attack. My doctors put me on three blood thinners to dissolve a clot in a minor artery seen in an angiogram. The next day, while the original clot had dissolved, I had a clot in a larger artery. Baffled, the cardiologists put in a stent. As they backed the scope out of the artery, it spasmed in another location.

At that time, I had a 4-year-old, an 8-year-old, and a 12-year-old. My husband traveled extensively for work. I asked myself two questions: 1) How do I feel about dying at age 39? 2) If I don’t die, how do I live?

Read More »

Dima’s story

March 3rd, 2021 was the day that changed everything. At 55, I had a busy counselling practice and a few other projects on the go. The pandemic was causing anxiety for many of my clients and in my private life. I had a lot of stress of my own: there were safety issues in the building where I lived, and I was looking for a new apt. Despite this, I thought I was handling it well. I was fairly healthy, I walked daily, ate well, meditated and didn’t smoke or drink.

I started to experience heavy fatigue towards the end of 2020 but told myself it was normal considering all that was going on in the world.

Read More »

Get Informed

Learn all about the symptoms, causes and triggers of these heart conditions.

Educate. Inform. Enlighten.
