
Menu
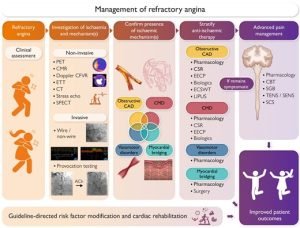
The diagnosis of refractory angina has conventionally been limited to patients with angina and ischaemia secondary to obstructive atherosclerotic epicardial coronary disease who experience persistent symptoms despite optimal pharmacological and revascularization therapies. It is now well-established that angina may also be caused by ischaemia resulting from coronary microcirculatory disorders, coronary vasospasm, and bridging in the absence of obstructive epicardial coronary disease or after “successful” revascularization.
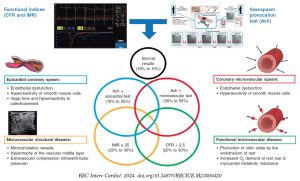
A substantial number of patients undergoing coronary angiography for angina or ischemia in noninvasive tests have coronary arteries without lesions or with nonsignificant stenosis. Many of these patients have nonobstructive myocardial ischemia (INOCA/ANOCA), which is an entity with prognostic importance that significantly affects patients’ quality of life.
The absence of a proper diagnosis leads to inappropriate medical treatment, repeat diagnostic tests, and greater use of social and health resources. An adequate diagnostic strategy is required for individualized treatment that improves symptoms and quality of life.
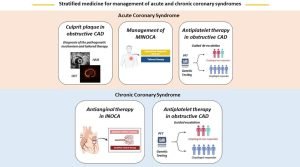
The traditional approach to management of cardiovascular disease relies on grouping clinical presentations with common signs and symptoms into pre-specified disease pathways, all uniformly treated according to evidence-based guidelines (“one-size-fits-all”). The goal of precision medicine is to provide the right treatment to the right patients at the right time, combining data from time honoured sources (e.g., history, physical examination, imaging, laboratory) and those provided by multi-omics technologies. In patients with ischemic heart disease, biomarkers and intravascular assessment can be used to identify endotypes with different pathophysiology who may benefit from distinct treatments. This review discusses strategies for the application of stratified management to patients with acute and chronic coronary syndromes.
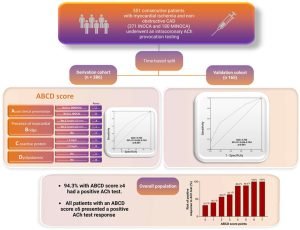
Acetylcholine (ACh) provocation testing can detect vasomotor disorders in patients with ischemia and non-obstructed coronary arteries (INOCA) or myocardial infarction and non-obstructed coronary arteries (MINOCA). We aimed to derive and validate a simple risk score to predict a positive ACh test response.
We prospectively enrolled consecutive INOCA and MINOCA patients undergoing ACh provocation testing. Patients were split in two cohorts (derivation and validation) according to time of enrolment. The score was derived in 386 patients (derivation cohort) and then validated in 165 patients (validation cohort).
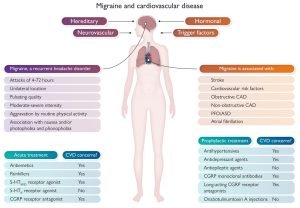
Migraine is a chronic neurovascular disease with a complex, not fully understood pathophysiology with multiple causes. People with migraine suffer from recurrent moderate to severe headache attacks varying from 4 to 72 h. The prevalence of migraine is two to three times higher in women compared with men.
Importantly, it is the most disabling disease in women over 50 years of age due to a high number of years lived with disability, resulting in a very high global socioeconomic burden. Robust evidence exists on the association between migraine with aura and increased incidence of cardiovascular disease (CVD), in particular ischaemic stroke. People with migraine with aura have an increased risk of atrial fibrillation, myocardial infarction, and cardiovascular death compared with those without migraine.

Ischemic heart disease continues to represent a major health threat for death, disability, and poor quality of life as it also consumes enormous health-related resources. For over a century, the major clinical phenotype was taken to be obstructive atherosclerosis involving the larger coronary arteries (e.g., coronary artery disease [CAD]). However, evolving evidence now indicates that nonobstructive CAD is the predominant phenotype.
Patients within this phenotype have been termed to have angina with no obstructive CAD (ANOCA), ischemia with no obstructive CAD (INOCA), or myocardial infarction with no obstructive coronary arteries (MINOCA). But as methods to assess cardiomyocyte injury evolve, these phenotypic distinctions have begun to merge, raising concern about their usefulness.

In the current review, we emphasize the importance of diagnostics and therapy in patients with ischaemia with no obstructive coronary arteries (INOCA).
The importance of the diagnostic coronary function test (CFT) procedure is described, including future components including angiography-derived physiology and invasive continuous thermodilution.

Nearly half of all patients with angina have non-obstructive coronary artery disease (ANOCA); this is an umbrella term comprising heterogeneous vascular disorders, each with disparate pathophysiology and prognosis. Approximately two-thirds of patients with ANOCA have coronary microvascular disease (CMD). CMD can be secondary to architectural changes within the microcirculation or secondary to vasomotor dysfunction.
An inability of the coronary vasculature to augment blood flow in response to heightened myocardial demand is defined as an impaired coronary flow reserve (CFR), which can be measured non-invasively, using imaging, or invasively during cardiac catheterisation. Impaired CFR is associated with myocardial ischaemia and adverse cardiovascular outcomes.

Up to half of patients undergoing elective coronary angiography for the investigation of chest pain do not present with evidence of obstructive coronary artery disease. These patients are often discharged with a diagnosis of non-cardiac chest pain, yet many could have an ischaemic basis for their symptoms. This type of ischaemic chest pain in the absence of obstructive coronary artery disease is referred to as INOCA (ischaemia with non-obstructive coronary arteries).
This comprehensive review of INOCA management looks at why these patients require treatment, who requires treatment based on diagnostic evaluation, what clinical treatment targets should be considered, how to treat patients using a personalised medicine approach, when to initiate treatment, and where future research is progressing.

Contemporary data indicate that patients with signs and symptoms of ischaemia and non-obstructive coronary artery disease (INOCA) often have coronary microvascular dysfunction (CMD) with elevated risk for adverse outcomes. Coronary endothelial (constriction with acetylcholine) and/or microvascular (limited coronary flow reserve with adenosine) dysfunction are well-documented, and extensive non-obstructive atherosclerosis is often present.
Despite these data, patients with INOCA currently remain under-treated, in part, because existing management guidelines do not address this large, mostly female population due to the absence of evidence-based data.

A new webinars series regarding myocardial ischaemia without obstructive coronary disease is now available on the IHSA website. This series of webinars was brought to you by PCRonline and is dedicated to the management of patients with ischemia and non-obstructive coronary artery disease.
The series includes 7 webinars where healthcare professionals discuss together many complex issues to educate others on INOCA.

At 4am, I woke up in the dark with crushing chest pain, nausea, shortness of breath, and pain radiating to my left arm and jaw. I was terrified. You would think that such symptoms would lead to a quick diagnosis. But as a young woman in my 20s who looked “healthy,” my journey to finally being diagnosed with Microvascular Angina was anything but easy.

Hello! My name is Jennifer, a 41-year-old mother of 5 and a nurse. My husband and I have been married nearly 15 years. Before I share my story, I’d like to share that I had never been on any medications other than Lexapro for mild depression and anxiety. I did not have heart problems or even high blood pressure. December 9, 2023, was the beginning of a life changing event leading to the diagnosis of Coronary Artery Spasm, also known as Prinzmetal Angina.

March 3rd, 2021 was the day that changed everything. At 55, I had a busy counselling practice and a few other projects on the go. The pandemic was causing anxiety for many of my clients and in my private life. I had a lot of stress of my own: there were safety issues in the building where I lived, and I was looking for a new apt. Despite this, I thought I was handling it well. I was fairly healthy, I walked daily, ate well, meditated and didn’t smoke or drink.
I started to experience heavy fatigue towards the end of 2020 but told myself it was normal considering all that was going on in the world.
Input your search keywords and press Enter.
