Category: Research

Research

Endotyping-informed therapy for patients with chest pain and no obstructive...

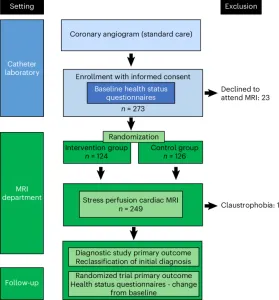
Patients undergoing invasive coronary angiography for the investigation of chest pain commonly do not have obstructive coronary artery disease. In contemporary practice, most of these individuals do not undergo functional diagnostic tests, leaving the cause of the chest pain uncertain. Stress cardiovascular magnetic resonance imaging (MRI) can be used to measure myocardial blood flow, detect coronary microvascular dysfunction and endotype individual patients, but evidence of clinical utility from randomized trials is lacking. This study was a prospective, multicenter, parallel group, 1:1 randomized, controlled superiority trial of adenosine stress cardiovascular MRI-guided management in 250 patients (mean age, 63.3 years; 50.4% female) with chest pain and unobstructed coronary arteries.

Read More »
Research

2023 ESC Guidelines for the management of acute coronary syndromes:...

Guidelines evaluate and summarize available evidence with the aim of assisting health professionals in proposing the best diagnostic or therapeutic approach for an individual patient with a given condition. Guidelines are intended for use by health professionals and the European Society of Cardiology (ESC) makes its Guidelines freely available. ESC Guidelines do not override the individual responsibility of health professionals to make appropriate and accurate decisions in consideration of each patient’s health condition and in consultation with that patient or the patient’s caregiver where appropriate and/or necessary.

Read More »
Research

Stratified treatment of myocardial infarction with non-obstructive coronary arteries: the...

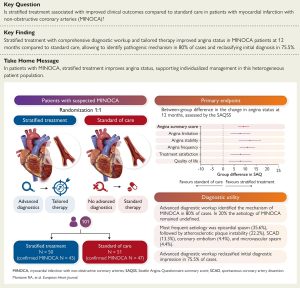
Myocardial infarction with non-obstructive coronary arteries (MINOCA) is associated with a significant risk of mortality, rehospitalization, and angina burden. Despite its clinical impact, no randomized clinical trials have hitherto evaluated optimal management strategy for MINOCA. The PROMISE trial was designed to assess whether a stratified treatment improves clinical outcomes in patients with MINOCA as compared to standard care.

Read More »
Research

Endotypes of angina with non-obstructive coronary arteries: a prospective multicentre...

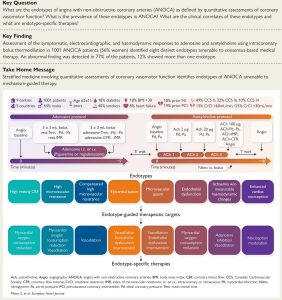
Angina and/or myocardial ischaemia with non-obstructive coronary arteries (ANOCA/INOCA) affects more than one in three individuals with stable ischaemic heart disease, and women are more often affected. This high prevalence of ANOCA, its impact on health-related quality of life and prognosis, and evidence supporting the role of invasive coronary function tests in persistently symptomatic patients have led to a class I recommendation in international practice guidelines and a call for further research into the diagnosis of this condition. As underlined in these guidelines, ANOCA/INOCA is ‘rarely correctly diagnosed and no tailored therapy is prescribed for these patients.’

Read More »
Research

Coronary Microvascular Dysfunction and Vasospastic Angina—Pathophysiology, Diagnosis and Management Strategies

Coronary artery disease is one of the leading public health problems in the world in terms of mortality and economic burden from the disease. Traditionally, the focus of research and clinical pathways leading to the diagnosis and treatment of coronary artery disease was on the more common variant of the disease resulting from atherosclerosis in the epicardial coronary arteries. However, coronary microvasculature, representing the vast majority of the total heart circulation, has the greatest influence on overall coronary resistance and, therefore, blood flow. Coronary microvascular dysfunction (CMD), characterized by structural or functional abnormalities in the microvasculature, significantly impacts myocardial perfusion. Endothelial dysfunction results in inadequate coronary dilation during exercise or spontaneous spasm in the microvasculature or epicardial arteries.

Read More »
Research

Coronary function testing vs angiography alone to guide treatment of...

Introduction

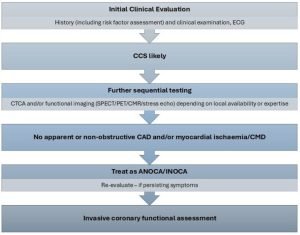
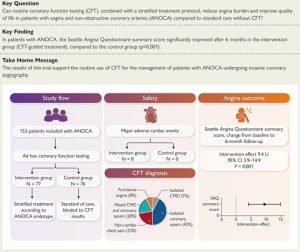
The diagnostic and therapeutic approach for patients with chronic coronary syndromes (CCS) is evolving from a simplistic approach focused on diagnosis and treatment of obstructive epicardial coronary artery disease (CAD) to include a comprehensive assessment of the functional status of the coronary circulation to assess causes of angina with non-obstructive coronary arteries (ANOCA).

ANOCA is present […]

Read More »
Research

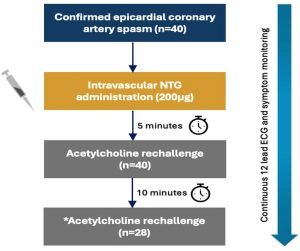
Impact of Nitroglycerin Administration on Acetylcholine Provocation Testing in Angina...

Introduction

Nearly half of all patients undergoing coronary angiography for stable angina are found to have nonobstructive coronary arteries. Invasive coronary function testing (CFT), using acetylcholine (ACh) to diagnose coronary artery spasm (CAS) and a pressure-temperature sensing guide wire to evaluate for coronary microvascular dysfunction (CMD), is considered the gold standard for evaluating patients with angina with […]

Read More »
Research

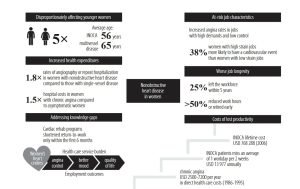
Societal, occupational, and economic considerations for women with (M)INOCA: a...

Cardiovascular disease is one of the leading causes of mortality in women, despite underrepresentation in the medical literature. Women have higher rates of ischemia and no obstructive coronary artery disease (INOCA) and myocardial infarction with no obstructive coronary artery disease (MINOCA) compared to men. The aim of this review is to describe the occupational, economic, and psychosocial factors which disproportionately impact women with (M)INOCA.

Read More »
Research

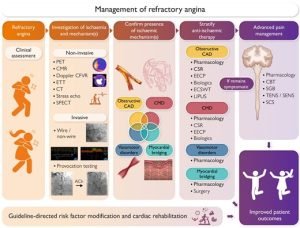
Refractory angina: mechanisms and stratified treatment in obstructive and non-obstructive...

The diagnosis of refractory angina has conventionally been limited to patients with angina and ischaemia secondary to obstructive atherosclerotic epicardial coronary disease who experience persistent symptoms despite optimal pharmacological and revascularization therapies. It is now well-established that angina may also be caused by ischaemia resulting from coronary microcirculatory disorders, coronary vasospasm, and bridging in the absence of obstructive epicardial coronary disease or after “successful” revascularization.

Read More »
Research

Functional Coronary Angiography for the Diagnosis of Coronary Vasomotor Disorders

Microvascular and/or vasospastic angina are two common forms of coronary vasomotor disorders that may occur in patients with ischaemia and non-obstructed coronary arteries (INOCA) or myocardial infarction with non-obstructive coronary arteries (MINOCA).

Functional coronary angiography involves invasive guidewire-based assessment of the coronary circulation using pharmacological vasoactive agents to assess small and large vasomotor dysfunction. Typically, responses to adenosine (microvascular vasodilator) and acetylcholine (large and small vessel vasospastic agent) are sequentially assessed.

Read More »
Research

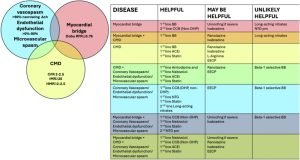
Current Evidence-Based Treatment of Angina With Nonobstructive Coronary Arteries (ANOCA)

Although the techniques for coronary function testing (CFT) were largely developed more than 30 years ago, consensus on the specific diagnostic criteria and endotypes is still lacking. Furthermore, the management of patients with angina with nonobstructive coronary arteries (ANOCA) is challenging for most cardiologists. These patients are often a burden to the health care system due to recurrent presentations to the emergency room, repeated coronary angiography, and lack of improvement in their anginal symptoms even after being properly diagnosed with CFT.

Read More »
Around The World

Real Patient Stories

MaryAnn’s story

When I was 39, with zero risk factors for heart disease, I had all the classic symptoms associated with a heart attack. My doctors put me on three blood thinners to dissolve a clot in a minor artery seen in an angiogram. The next day, while the original clot had dissolved, I had a clot in a larger artery. Baffled, the cardiologists put in a stent. As they backed the scope out of the artery, it spasmed in another location.

At that time, I had a 4-year-old, an 8-year-old, and a 12-year-old. My husband traveled extensively for work. I asked myself two questions: 1) How do I feel about dying at age 39? 2) If I don’t die, how do I live?

Read More »

Charlotte’s story

While at work in September 2014, I lost vision of my left eye and had terrible feeling of “heat” all over the left side of my body.

The ER ophthalmologist directed me to cardiology for a vascular problem.

A week later, I could not walk 100 meters (325 feet) without crushing chest pain and shortness of breath.

I was no longer functional. Making my bed was all I could do in a whole day. I was no longer an active 54-year-old.

Read More »

Barbara’s story

I am a 62-year-old retired physician. My story began at age 47.

I was a very busy practicing OB/Gyn physician who was otherwise healthy.

I was on call at the hospital, and it was turning out to be one of the busiest days I had ever experienced as a physician. I was in a medical group that took call for 24 hours straight, most of the time working the entire 24 hours.

Halfway through that 24-hour call, I was in the operating room doing a C/Section on a patient. Halfway through the surgery I began to feel crushing chest pain.

Read More »

Get Informed

Learn all about the symptoms, causes and triggers of these heart conditions.

Educate. Inform. Enlighten.