Latest News

What's New

Recent Articles

Research

Characterizing Mechanisms of Ischemia in Patients With Myocardial Bridges

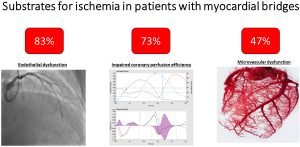
Myocardial bridges (MBs) are prevalent and can be associated with acute and chronic ischemic syndromes. We sought to determine the substrates for ischemia in patients with angina with nonobstructive coronary arteries and a MB in the left anterior descending artery.

Patients with angina with nonobstructive coronary arteries underwent the acquisition of intracoronary pressure and flow during rest, supine bicycle exercise, and adenosine infusion. Coronary wave intensity analysis was performed, with perfusion efficiency defined as accelerating wave energy/total wave energy (%).

Read More »
Research

Predicting the response to acetylcholine in ischemia or infarction with...

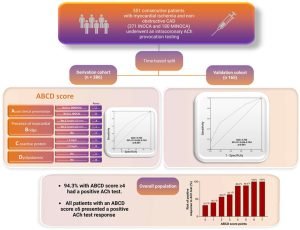
Acetylcholine (ACh) provocation testing can detect vasomotor disorders in patients with ischemia and non-obstructed coronary arteries (INOCA) or myocardial infarction and non-obstructed coronary arteries (MINOCA). We aimed to derive and validate a simple risk score to predict a positive ACh test response.

We prospectively enrolled consecutive INOCA and MINOCA patients undergoing ACh provocation testing. Patients were split in two cohorts (derivation and validation) according to time of enrolment. The score was derived in 386 patients (derivation cohort) and then validated in 165 patients (validation cohort).

Read More »
Research

Rethinking the Meaning of IHD: Invasive Assessment of ANOCA

Ischemic cardiovascular disease (IHD) continues to be a significant public health problem in the U.S. Typically, ischemia is associated with epicardial coronary artery obstruction caused by atherosclerotic plaque. Angina pectoris, the most common symptom of IHD, affects approximately 112 million people globally.

However, in up to two-thirds of patients undergoing coronary angiography because of angina and evidence of myocardial ischemia, there is no proof of obstructive coronary artery diseases (CAD).

Read More »
Research

Vasospastic angina: a review on diagnostic approach and management

Vasospastic angina (VSA) refers to chest pain experienced as a consequence of myocardial ischaemia caused by epicardial coronary spasm, a sudden narrowing of the vessels responsible for an inadequate supply of blood and oxygen. Coronary artery spasm is a heterogeneous phenomenon that can occur in patients with non-obstructive coronary arteries and obstructive coronary artery disease, with transient spasm causing chest pain and persistent spasm potentially leading to acute myocardial infarction (MI).

VSA was originally described as Prinzmetal angina or variant angina, classically presenting at rest, unlike most cases of angina (though in some patients, vasospasm may be triggered by exertion, emotional, mental or physical stress), and associated with transient electrocardiographic changes (transient ST-segment elevation, depression and/or T-wave changes).

Read More »
Research

Living with myocardial ischaemia and no obstructive coronary arteries: a...

Coronary artery disease is traditionally characterised by obstructive atherosclerosis. However, up to two in five people experience symptoms of myocardial ischaemia without obstructive coronary artery disease. This condition can be caused by a range of underlying pathologies including coronary endothelial dysfunction, microvascular remodelling, microvascular and epicardial spasm and vasomotor abnormalities.

A range of medical terms is used to describe distinct aspects of these conditions, including microvascular angina, coronary microvascular dysfunction, vasospastic angina, coronary vasospasms, coronary artery spasms, prinzmetal/variant angina and angina/ischaemia with no obstructive coronary arteries (ANOCA/INOCA). Women are disproportionately affected, particularly over the age of 40 years.

Read More »
Research

Coronary spasm and vasomotor dysfunction as a cause of MINOCA

Increasing evidence has shown that coronary spasm and vasomotor dysfunction may be the underlying cause in more than half of myocardial infarctions with non-obstructive coronary arteries (MINOCA) as well as an important cause of chronic chest pain in the outpatient setting. We review the contemporary understanding of coronary spasm and related vasomotor dysfunction of the coronary arteries, the pathophysiology and prognosis, and current and emerging approaches to diagnosis and evidence-based treatment.

Read More »
Research

Rethinking False Positive Exercise Electrocardiographic Stress Tests by Assessing Coronary...

Exercise electrocardiographic stress testing (EST) has historically been validated against the demonstration of obstructive coronary artery disease. However, myocardial ischemia can occur because of coronary microvascular dysfunction (CMD) in the absence of obstructive coronary artery disease.

The aim of this study was to assess the specificity of EST to detect an ischemic substrate against the reference standard of coronary endothelium-independent and endothelium-dependent microvascular function in patients with angina with nonobstructive coronary arteries (ANOCA).

Read More »
Research

A Short History of Vasospastic Angina

The syndrome of chest pain and/or myocardial ischemia with normal or nonobstructive coronary arteries at angiography is common and is of practical importance to the general medical audience. Many studies have tried to address this topic over the last 4 decades. Only 1 thing is clear: for patients with ongoing signs and symptoms of ischemia in acute coronary syndromes, the prognosis is not so favorable, as believed earlier in the 1990s. Yet, physicians remain confused by other patients who refer a history of effort angina or angina-like chest pain whose coronary angiograms show no evidence of obstructive coronary artery disease (CAD) and who have no structural heart disease.

Read More »
Research

ChaMP-CMD: A Phenotype-Blinded, Randomized Controlled, Cross-Over Trial

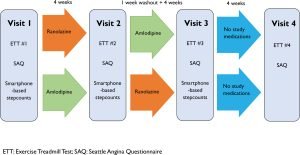
Angina with nonobstructive coronary arteries is a common condition for which no effective treatment has been established. We hypothesized that the measurement of coronary flow reserve (CFR) allows identification of patients with angina with nonobstructive coronary arteries who would benefit from anti-ischemic therapy.

Patients with angina with nonobstructive coronary arteries underwent blinded invasive CFR measurement and were randomly assigned to receive 4 weeks of amlodipine or ranolazine. After a 1-week washout, they crossed over to the other drug for 4 weeks; final assessment was after the cessation of study medication for another 4 weeks.

Read More »
Research

Invasive Endotyping in Patients With Angina and No Obstructive Coronary...

We investigated the usefulness of invasive coronary function testing to diagnose the cause of angina in patients with no obstructive coronary arteries.

Outpatients referred for coronary computed tomography angiography in 3 hospitals in the United Kingdom were prospectively screened. After coronary computed tomography angiography, patients with unobstructed coronary arteries, and who consented, underwent invasive endotyping.

Read More »
Around The World

Real Patient Stories

Don’s story

I consider myself one of the lucky ones.

I was a runner, triathlete, skier, scuba diver, etc. before my problems got severe enough to seek medical help.

Most doctors took my health decline seriously from the start.

Later, it was not uncommon for doctors who were unaware of my athletic endeavours to assume my subsequent lack of fitness was the cause of my condition rather than the result.

Read More »

MaryAnn’s story

When I was 39, with zero risk factors for heart disease, I had all the classic symptoms associated with a heart attack. My doctors put me on three blood thinners to dissolve a clot in a minor artery seen in an angiogram. The next day, while the original clot had dissolved, I had a clot in a larger artery. Baffled, the cardiologists put in a stent. As they backed the scope out of the artery, it spasmed in another location.

At that time, I had a 4-year-old, an 8-year-old, and a 12-year-old. My husband traveled extensively for work. I asked myself two questions: 1) How do I feel about dying at age 39? 2) If I don’t die, how do I live?

Read More »

Charlotte’s story

While at work in September 2014, I lost vision of my left eye and had terrible feeling of “heat” all over the left side of my body.

The ER ophthalmologist directed me to cardiology for a vascular problem.

A week later, I could not walk 100 meters (325 feet) without crushing chest pain and shortness of breath.

I was no longer functional. Making my bed was all I could do in a whole day. I was no longer an active 54-year-old.

Read More »

Get Informed

Learn all about the symptoms, causes and triggers of these heart conditions.

Educate. Inform. Enlighten.